For decades, cholesterol testing has been a little like judging a restaurant by the number of chairs inside. Useful? Yes. Complete? Not always. A standard lipid panel tells you total cholesterol, LDL cholesterol, HDL cholesterol, and triglycerides. Those numbers matter. But heart health experts are increasingly paying attention to another test that may reveal hidden cardiovascular risk: the apoB test.
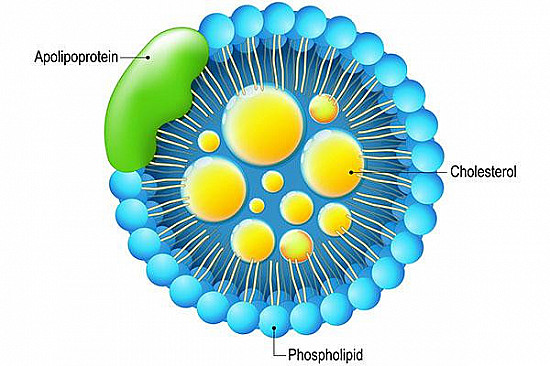
ApoB, short for apolipoprotein B, measures the number of harmful cholesterol-carrying particles in your blood. Instead of asking, “How much cholesterol is riding around?” apoB asks, “How many tiny delivery trucks are carrying artery-clogging cargo?” That distinction can be important because two people can have the same LDL cholesterol level but very different numbers of cholesterol particles. One person may have fewer large particles; another may have many smaller particles. The second person may face a higher risk of plaque buildup, even if their LDL number looks deceptively normal.
So, is an apoB test a better way to check your cholesterol? The most practical answer is: for many people, it can be a better add-on test, especially when the standard cholesterol panel does not tell the whole story. It is not necessarily a replacement for LDL cholesterol, but it may help sharpen the picture of heart disease risk.
What Is an apoB Test?
An apoB test is a simple blood test that measures apolipoprotein B, a protein found on the surface of several atherogenic lipoproteins. “Atherogenic” is the medical term for particles that can contribute to atherosclerosis, the slow buildup of fatty plaque inside artery walls. Think of apoB as the license plate on cholesterol particles that are most likely to cause trouble.
The major apoB-containing particles include LDL, VLDL, IDL, remnants, and lipoprotein(a). Each of these particles generally carries one apoB molecule. That means your apoB level can act as a rough count of the number of potentially artery-damaging particles circulating in your bloodstream.
LDL Cholesterol vs. apoB: What Is the Difference?
LDL cholesterol measures the amount of cholesterol inside LDL particles. ApoB measures the number of particles that carry cholesterol and other fats. This is where the plot thickens. LDL cholesterol is like measuring the total weight of packages in delivery trucks. ApoB counts the trucks.
Why does that matter? Arteries do not care only about how much cholesterol is inside each particle. They also care about how many particles repeatedly bump into the artery wall. More apoB-containing particles create more opportunities for cholesterol to enter the artery wall, trigger inflammation, and form plaque.
In many people, LDL cholesterol and apoB move together. If LDL is high, apoB is often high too. But in some people, especially those with insulin resistance, type 2 diabetes, metabolic syndrome, abdominal weight gain, or high triglycerides, LDL and apoB can become “discordant.” In plain English, the LDL number may look acceptable while the apoB number waves a tiny red flag.
Why Harvard Health and Cardiologists Are Talking About apoB
Harvard Health and other major heart health organizations have highlighted apoB because research suggests it may be more closely linked to cardiovascular risk than LDL cholesterol alone in certain situations. This does not mean LDL cholesterol is suddenly useless. LDL is still central to cholesterol screening, treatment decisions, and long-term prevention. But apoB may give clinicians a more direct estimate of the number of harmful particles that can enter artery walls.
In everyday terms, apoB can be especially helpful when the usual cholesterol numbers look a bit too neat and tidy for a person’s real-life risk profile. For example, someone may have an LDL cholesterol level that appears “near normal,” but they also have high triglycerides, prediabetes, a family history of early heart disease, and a waistline that keeps trying to negotiate with their belt. In that case, apoB may uncover a higher particle burden than LDL suggests.
Who Might Benefit Most From an apoB Test?
Not everyone needs an apoB test. Many people can be assessed well with a standard lipid panel, blood pressure measurement, diabetes screening, smoking history, family history, and an overall cardiovascular risk calculator. However, apoB testing may be particularly useful for several groups.
People With High Triglycerides
High triglycerides often travel with a cluster of smaller, cholesterol-poor but particle-rich lipoproteins. In that situation, LDL cholesterol can underestimate risk because the cholesterol content per particle may be lower, while the number of particles remains high. ApoB helps reveal that particle count.
People With Type 2 Diabetes or Prediabetes
Diabetes and insulin resistance can change the way the body packages and clears lipoproteins. A person with diabetes may have LDL cholesterol that does not look alarming, yet their apoB may be elevated. This is one reason apoB can be useful in metabolic health assessment.
People With Metabolic Syndrome
Metabolic syndrome usually refers to a combination of abdominal obesity, high blood pressure, high blood sugar, high triglycerides, and low HDL cholesterol. This pattern is strongly linked with a higher number of atherogenic particles. ApoB can help show whether the particle burden is higher than a standard panel suggests.
People With a Strong Family History of Early Heart Disease
If a parent, sibling, or close relative had a heart attack or stroke at a young age, a more detailed cholesterol evaluation may be worthwhile. ApoB can be one part of that deeper look, along with lipoprotein(a), LDL cholesterol, non-HDL cholesterol, blood pressure, glucose, and lifestyle factors.
People Already Taking Cholesterol-Lowering Medication
For people on statins or other lipid-lowering therapy, apoB may help assess whether enough atherogenic particles remain in circulation. LDL cholesterol may reach a target while apoB remains higher than expected in some patients, especially those with high triglycerides or diabetes.
What Do apoB Results Mean?
Interpretation depends on your overall cardiovascular risk, medical history, and the laboratory reference range. Many labs consider an adult apoB level below 90 mg/dL desirable. Levels above that may be described as above desirable, borderline high, high, or very high depending on the exact number and the lab’s categories.
Some cardiology guidance and lipid experts suggest lower apoB goals for people at higher risk. For instance, a person with known heart disease, diabetes, or multiple risk factors may need a lower apoB target than someone who is young, healthy, and at low short-term risk. This is why apoB should not be interpreted like a school grade where 89 is always “good” and 91 is always “bad.” Your personal risk context matters.
Is apoB Better Than LDL Cholesterol?
ApoB may be better than LDL cholesterol at estimating risk when LDL and particle number do not match. That is the key point. LDL cholesterol tells you how much cholesterol is carried inside LDL particles. ApoB tells you how many atherogenic particles are present. When those two numbers agree, apoB may not add much. When they disagree, apoB can be very useful.
Here is a simple example. Imagine two people with an LDL cholesterol level of 110 mg/dL. Person A has fewer LDL particles, each carrying more cholesterol. Person B has many more particles, each carrying less cholesterol. Their LDL cholesterol looks the same on paper, but Person B may have a higher apoB level and potentially higher cardiovascular risk. The standard LDL number alone may miss that difference.
That said, apoB is not magic. It does not replace a thoughtful medical evaluation. Blood pressure, smoking, age, kidney function, diabetes, inflammatory conditions, family history, physical activity, diet, sleep, and body weight all matter. Heart disease risk is a group project, unfortunately, and cholesterol is only one member of the team.
How Is the apoB Test Done?
The apoB test is usually performed with a standard blood draw. In many cases, fasting is not required, although your clinician may ask you to fast if triglycerides are being checked at the same time or if previous results were very high. The test can be ordered along with a lipid panel, advanced lipid testing, lipoprotein(a), A1C, or other cardiovascular risk markers.
Some direct-to-consumer lab services offer apoB testing, but it is best to discuss the result with a qualified healthcare professional. A number by itself can cause either false reassurance or unnecessary panic. The goal is not to collect fancy biomarkers like baseball cards. The goal is to use the right information to make better prevention decisions.
What Can You Do If apoB Is High?
If your apoB is elevated, the next step is not to throw your pantry into a bonfire and start jogging in dress shoes. The next step is to review your overall risk and build a realistic plan. In many cases, the same strategies that lower LDL cholesterol and triglycerides can also reduce apoB.
Eat More Soluble Fiber
Soluble fiber helps reduce cholesterol absorption in the digestive tract. Oats, beans, lentils, apples, barley, chia seeds, and psyllium are common sources. A bowl of oatmeal will not single-handedly defeat cardiovascular disease, but it is a much better breakfast teammate than a frosted pastry the size of a paperback novel.
Choose Unsaturated Fats More Often
Replacing saturated fats with unsaturated fats can improve LDL cholesterol and apoB-related risk. Practical swaps include using olive oil instead of butter, eating nuts instead of chips, choosing fish instead of processed meats, and adding avocado or seeds in reasonable portions.
Reduce Refined Carbohydrates and Added Sugars
For people with high triglycerides, insulin resistance, or fatty liver risk, cutting back on sugary drinks, sweets, white bread, and highly processed snacks can make a meaningful difference. This does not mean carbohydrates are villains wearing tiny capes. It means quality and quantity matter.
Exercise Consistently
Regular physical activity can improve triglycerides, insulin sensitivity, blood pressure, HDL cholesterol, and weight management. A mix of aerobic exercise and resistance training is ideal. Walking counts. Dancing in the kitchen counts. Carrying every grocery bag in one trip may count emotionally, but your shoulders may disagree.
Consider Medication When Risk Is High
For some people, lifestyle changes are not enough. Statins remain the first-line medication for many patients at elevated cardiovascular risk because they lower LDL cholesterol and reduce heart attack and stroke risk. Other options may include ezetimibe, PCSK9 inhibitors, bempedoic acid, or other therapies depending on the person’s risk profile and response to treatment.
apoB, Non-HDL Cholesterol, and Lipoprotein(a): How They Fit Together
Non-HDL cholesterol is another useful number from a standard lipid panel. It is calculated by subtracting HDL cholesterol from total cholesterol. Non-HDL cholesterol includes cholesterol carried by LDL, VLDL, remnants, and other atherogenic particles. It is often more informative than LDL cholesterol when triglycerides are elevated.
Lipoprotein(a), often written as Lp(a), is a genetically influenced cholesterol-carrying particle that can raise cardiovascular risk. Unlike apoB, which reflects the number of several harmful particles, Lp(a) measures a specific inherited particle. Many experts now encourage broader Lp(a) testing at least once in adulthood, especially when there is family history of early heart disease.
ApoB, non-HDL cholesterol, and Lp(a) are not competitors in a cholesterol talent show. They answer different questions. LDL cholesterol asks how much cholesterol is in LDL particles. Non-HDL cholesterol asks how much cholesterol is in all “non-good” particles. ApoB asks how many atherogenic particles are present. Lp(a) asks whether you have a specific inherited risk-enhancing particle.
Should You Ask Your Doctor for an apoB Test?
It may be worth asking if you have high triglycerides, type 2 diabetes, prediabetes, metabolic syndrome, obesity, a strong family history of early cardiovascular disease, or confusing cholesterol results. It may also be helpful if you are already on treatment and want to understand whether your remaining particle-related risk is well controlled.
When you talk with your clinician, ask practical questions: What does my apoB add to my standard lipid panel? Does it change my risk category? Would it change my treatment plan? What target makes sense for me? Should I also check Lp(a)? How often should this be repeated?
A good test should lead to a better decision. If the apoB result does not change what you do, it may not be necessary. If it clarifies uncertainty or reveals hidden risk, it may be extremely useful.
Common Myths About apoB Testing
Myth 1: “If My LDL Is Normal, I Am Definitely Fine.”
Not always. Normal LDL cholesterol is reassuring, but it does not guarantee low risk. ApoB may be elevated in some people with normal or near-normal LDL, especially when triglycerides are high or metabolic health is impaired.
Myth 2: “apoB Is Only for Biohackers.”
Nope. ApoB is used by lipid specialists, cardiologists, and primary care clinicians when a deeper cardiovascular risk assessment is needed. It sounds futuristic, but it is a regular blood test, not a spaceship dashboard.
Myth 3: “A High apoB Means I Am Doomed.”
A high apoB means there may be more atherogenic particles in your blood than ideal. It is a risk marker, not a prophecy. Diet, exercise, weight management, smoking cessation, blood pressure control, diabetes management, and medication can all help reduce risk.
Real-Life Experience: What It Feels Like to Use apoB in Cholesterol Decisions
Imagine a person named Mark, age 48, who gets his annual physical and feels pretty good about himself. He walks the dog, plays weekend pickleball, and only occasionally eats nachos as if training for a competitive cheese event. His LDL cholesterol comes back at 112 mg/dL. Not perfect, but not terrifying. His doctor notices something else: triglycerides at 210 mg/dL, HDL cholesterol on the low side, fasting glucose creeping upward, and a father who had a heart attack at 57.
On paper, Mark’s LDL alone might not cause immediate alarm. But his overall pattern suggests insulin resistance and a potentially higher number of atherogenic particles. His doctor orders an apoB test. The result is 118 mg/dL, higher than expected. Suddenly, the conversation changes. Not into a panic session, but into a clearer discussion. Mark sees that his “not too bad” LDL number was not the whole movie; it was just the trailer.
With that information, Mark and his clinician build a plan. He starts by reducing sugary drinks, replacing late-night chips with Greek yogurt and berries, adding beans and vegetables to lunches, and walking briskly after dinner. He also begins resistance training twice a week because muscle is not just for looking confident while opening pickle jars. After a follow-up discussion, he starts a statin because his family history and metabolic pattern make prevention more urgent.
Three months later, Mark repeats his labs. His LDL cholesterol is lower, triglycerides have improved, and apoB has dropped. More importantly, Mark understands why the plan exists. He is not just chasing a cholesterol number; he is lowering the number of harmful particles that can contribute to plaque. That understanding makes the plan easier to follow.
Now consider a different person, Elena, age 39. She eats well, runs three times a week, and has an LDL cholesterol of 96 mg/dL. Her triglycerides are normal, blood pressure is excellent, and she has no diabetes. She asks for apoB because she heard about it on a podcast. Her apoB comes back low. In her case, the test confirms what the rest of her profile already suggested: low particle burden and low short-term risk. The result is useful, but it does not dramatically change her plan.
Then there is Denise, age 62, who already takes a statin after a small heart attack. Her LDL cholesterol reaches a guideline-based goal, but her triglycerides remain elevated and she has type 2 diabetes. Her clinician checks apoB to see whether residual atherogenic particle risk remains. The apoB result helps guide whether to intensify therapy, adjust lifestyle priorities, or add another medication. For Denise, apoB becomes a monitoring tool, not just a one-time curiosity.
These experiences show the real value of apoB: context. The test is most powerful when it answers a specific question. Is my LDL cholesterol underestimating risk? Do my triglycerides and metabolic markers suggest more particles than expected? Is my treatment lowering the number of harmful particles enough? When apoB is used this way, it can make cholesterol care feel less like a guessing game and more like a personalized prevention strategy.
The best cholesterol test is not always the newest one. It is the one that helps you and your healthcare professional make the smartest next decision. For many people, that still starts with a standard lipid panel. For others, especially those with metabolic risk or confusing numbers, apoB may be the missing clue.
Conclusion: Is apoB a Better Cholesterol Test?
An apoB test can be a better way to understand cholesterol-related heart risk for people whose standard lipid panel may not tell the whole story. It measures the number of harmful cholesterol-carrying particles, which may be more closely tied to plaque buildup than LDL cholesterol alone in certain groups.
Still, apoB is not a replacement for medical judgment. LDL cholesterol, non-HDL cholesterol, triglycerides, blood pressure, glucose, family history, and lifestyle all matter. The smartest approach is not “LDL or apoB.” It is using the right tools for the right person at the right time.
Medical note: This article is for educational purposes only and should not replace professional medical advice. If you are concerned about cholesterol, apoB, or cardiovascular risk, talk with a licensed healthcare professional who can interpret your results based on your full health history.