Chronic lymphocytic leukemia can sound like three intimidating medical words standing on one another’s shoulders in a trench coat. Fortunately, understanding the name makes the condition much less mysterious.
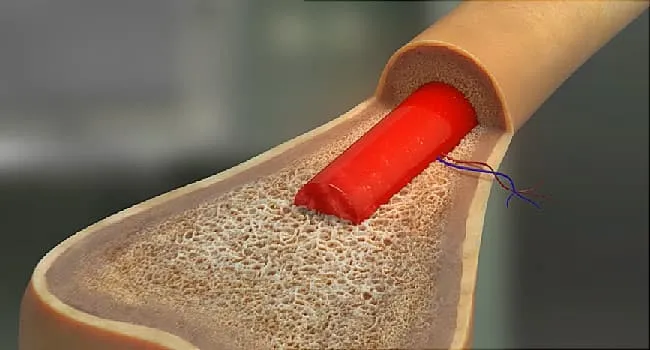
Chronic lymphocytic leukemia, commonly shortened to CLL, is a cancer of certain white blood cells called lymphocytes. It usually begins in the bone marrow, where blood cells are produced, and then appears in the bloodstream. Over time, abnormal lymphocytes may also collect in the lymph nodes, spleen, liver, and other tissues.
The word “chronic” means that CLL usually develops more slowly than acute leukemia. “Lymphocytic” identifies the type of blood cell involved. “Leukemia” means the cancer primarily affects blood-forming tissues and circulating blood cells.
Many people with CLL feel completely well when it is discovered. In fact, a routine blood test may detect it long before symptoms appear. Some people remain stable without treatment for years, while others have a faster-growing form that requires therapy sooner. CLL is therefore less like a single highway and more like a network of roads, complete with slow lanes, express lanes, and the occasional confusing exit.
Evidence basis:
How Chronic Lymphocytic Leukemia Develops
Healthy bone marrow continually produces red blood cells, platelets, and several types of white blood cells. Lymphocytes are white blood cells that help the immune system recognize and respond to infections. They include B cells, T cells, and natural killer cells.
Almost all cases of CLL involve B lymphocytes. Genetic changes cause one abnormal B cell to multiply into a large population of nearly identical cells. These CLL cells may resemble mature lymphocytes, but they do not function normally. They also survive longer than they should, rather like houseguests who have forgotten both the time and the location of the front door.
As abnormal cells accumulate, they can crowd healthy blood-forming cells in the bone marrow. This may eventually reduce the production of:
- Red blood cells, leading to anemia, weakness, or shortness of breath.
- Healthy white blood cells and antibodies, increasing susceptibility to infection.
- Platelets, causing easy bruising, prolonged bleeding, or small red skin spots called petechiae.
The abnormal lymphocytes may also enlarge lymph nodes or the spleen. However, having a high white blood cell count does not mean the immune system has become supercharged. The extra cells are often poor infection fighters, despite arriving in impressive numbers.
Evidence basis:
CLL and Small Lymphocytic Lymphoma
Chronic lymphocytic leukemia and small lymphocytic lymphoma, or SLL, are generally considered different presentations of the same disease. The cancer cells share the same appearance and biological features.
The main distinction is where most of the abnormal cells are found:
- In CLL, the cells are concentrated in the blood and bone marrow.
- In SLL, they are found mainly in lymph nodes, the spleen, or other lymphatic tissues, with fewer abnormal cells circulating in the blood.
Because the two conditions are so closely connected, healthcare professionals frequently refer to them together as CLL/SLL. Their treatment approaches are also largely the same.
Evidence basis:
Who Is Most Likely to Develop CLL?
CLL primarily affects older adults. Current U.S. cancer data place the median age at diagnosis at approximately 71, and the condition is most frequently diagnosed among people between 65 and 74. It is uncommon in adults younger than 40 and exceptionally rare in children.
Men are diagnosed more often than women. Rates are also higher among non-Hispanic White adults than among many other racial and ethnic groups in the United States. These patterns may involve inherited susceptibility, environmental influences, and biological differences that researchers are still working to understand.
Known CLL risk factors
Factors associated with a higher likelihood of developing CLL include:
- Older age.
- Being male.
- A close relative with CLL or another blood or bone marrow cancer.
- Having monoclonal B-cell lymphocytosis, or MBL.
- Exposure to certain chemicals, including Agent Orange.
MBL is a condition in which a small population of abnormal B cells is found in the blood without enough cells or other findings to meet the definition of CLL. Most people with MBL never develop leukemia, although doctors may recommend periodic monitoring.
For most patients, no single cause can be identified. CLL is not contagious, and it is not usually possible to trace the diagnosis to a particular food, stressful week, missed workout, or other personal choice.
Evidence basis:
Symptoms of Chronic Lymphocytic Leukemia
Many people have no CLL symptoms at diagnosis. The condition may first appear as an elevated lymphocyte count on a complete blood count ordered during a physical examination, before surgery, or while investigating an unrelated concern.
When symptoms develop, they may include:
- Painless swelling of lymph nodes in the neck, armpits, abdomen, or groin.
- Persistent or significant fatigue.
- Frequent, severe, or unusually slow-to-resolve infections.
- Fever without an obvious infection.
- Drenching night sweats.
- Unintentional weight loss.
- Reduced appetite.
- Easy bruising or bleeding.
- Shortness of breath during ordinary activity.
- Pressure, discomfort, or fullness below the left ribs from an enlarged spleen.
These symptoms are not specific to leukemia. Fatigue, for example, has an extensive résumé and can accompany everything from anemia to inadequate sleep. Persistent or unexplained symptoms should nevertheless be evaluated rather than diagnosed through an online guessing contest.
Evidence basis:
How CLL Is Diagnosed
A CLL diagnosis often begins with a complete blood count, or CBC, showing an elevated number of lymphocytes. A healthcare professional will also review symptoms, medical history, family history, medications, and possible exposures. The physical examination may focus on lymph nodes and the size of the liver or spleen.
Complete blood count and blood smear
The CBC measures white blood cells, red blood cells, hemoglobin, and platelets. A peripheral blood smear allows laboratory specialists to examine the cells under a microscope. CLL may produce numerous small lymphocytes and fragile cells commonly called smudge cells.
A persistent count of at least 5,000 clonal B lymphocytes per microliter of blood supports a diagnosis of CLL, but the number alone is not enough. Other causes of lymphocytosis must be excluded, and the cells must have the characteristic CLL pattern.
Flow cytometry
Flow cytometry is one of the most important CLL tests. It examines proteins on the surface of blood cells and determines whether the B lymphocytes form an abnormal clone. CLL cells commonly display a recognizable combination of markers, including CD5, CD19, CD20, and CD23.
Genetic and molecular testing
Tests such as fluorescence in situ hybridization, or FISH, can look for chromosome changes within the CLL cells. Doctors may also test for a TP53 mutation and determine whether the immunoglobulin heavy-chain variable region gene, known as IGHV, is mutated or unmutated.
Changes such as deletion 17p or a TP53 mutation may indicate that the disease is more difficult to control with certain therapies. These results help guide treatment selection and should often be reassessed when therapy is being considered.
Are bone marrow biopsies and scans always necessary?
No. Blood testing is often sufficient to diagnose CLL. A bone marrow biopsy may be used when the diagnosis is unclear, before certain treatments, or when a doctor needs more information about low blood counts.
CT or PET scans are not automatically required for every newly diagnosed patient. Imaging may be helpful when internal lymph nodes are a concern, treatment planning requires additional detail, or rapidly growing nodes and systemic symptoms raise concern about transformation into a more aggressive lymphoma.
Evidence basis:
Understanding CLL Stages and Prognosis
CLL is not usually staged with the familiar solid-tumor system of stages I through IV based on tumor size and distant spread. In the United States, clinicians commonly use the Rai staging system:
- Rai stage 0: Increased lymphocytes without enlarged nodes, anemia, or low platelets.
- Rai stage I: Increased lymphocytes with enlarged lymph nodes.
- Rai stage II: Enlargement of the spleen or liver, with or without enlarged lymph nodes.
- Rai stage III: Anemia related to the leukemia.
- Rai stage IV: A low platelet count related to the leukemia.
The Binet system, used more often in Europe, groups CLL into stages A, B, and C according to the number of involved lymphoid areas and whether anemia or thrombocytopenia is present.
Stage is only one part of the outlook. Doctors also consider age, general health, symptoms, lymphocyte doubling time, beta-2 microglobulin, IGHV status, TP53 changes, chromosome findings, and response to previous treatment.
Population statistics cannot predict one person’s future. They combine people with different stages, biological risk factors, health conditions, and treatments. Still, national data show that many people live with CLL for years, and outcomes have improved substantially with modern targeted therapies.
Evidence basis:
Why Some People Do Not Need Immediate Treatment
One of the most surprising features of CLL care is that a confirmed cancer diagnosis may be followed by no immediate cancer treatment. This approach is called active surveillance, observation, or “watch and wait.”
Active surveillance is not the same as ignoring the disease. Patients have scheduled appointments, physical examinations, symptom reviews, and blood tests. The care team watches for meaningful changes rather than launching treatment simply because leukemia cells are present.
Treatment may be recommended when CLL causes problems such as:
- Worsening anemia or a falling platelet count.
- Progressively enlarging or uncomfortable lymph nodes.
- A rapidly enlarging spleen.
- Significant fatigue that limits normal activities.
- Persistent fevers, drenching night sweats, or substantial weight loss.
- Rapid disease progression.
- Autoimmune blood-cell destruction that is difficult to control.
A high lymphocyte count by itself does not automatically require therapy. Doctors interpret the count alongside symptoms, other blood values, genetic findings, and how quickly the disease is changing.
Evidence basis:
How Chronic Lymphocytic Leukemia Is Treated
Modern CLL treatment is increasingly personalized. The best option depends on the leukemia’s genetic characteristics, previous treatments, heart and kidney health, other medications, infection risk, age, and patient preferences.
Targeted therapy
Targeted drugs have become central to CLL care. Bruton tyrosine kinase inhibitors, or BTK inhibitors, interfere with signals that help CLL cells survive. Examples include acalabrutinib, zanubrutinib, and ibrutinib.
Venetoclax blocks BCL-2, a protein that helps leukemia cells avoid programmed cell death. It is often combined with an anti-CD20 monoclonal antibody such as obinutuzumab. Some regimens continue until the disease progresses, while others are designed to last for a fixed period.
Treatment choice involves trade-offs. Continuous therapy may offer convenience in some situations but requires ongoing medication. Fixed-duration treatment provides a planned stopping point but may require closer monitoring at the beginning because rapidly dying cancer cells can cause tumor lysis syndrome.
Immunotherapy and monoclonal antibodies
Monoclonal antibodies attach to proteins on B cells and help the immune system recognize or destroy them. Rituximab and obinutuzumab are common examples used in combination with other treatments.
Chemotherapy
Chemotherapy is used less frequently than it once was because targeted treatments are effective for many patients and may be better suited to specific genetic risk groups. Chemoimmunotherapy remains an option in selected circumstances, particularly when targeted drugs are unsuitable or previous therapies are no longer effective.
CAR T-cell therapy and stem cell transplantation
CAR T-cell therapy modifies a patient’s own T cells so they can recognize and attack cancer cells. It may be considered for selected people with CLL that has returned or stopped responding after multiple treatments.
An allogeneic stem cell transplant can offer long-term disease control and may be potentially curative for a small number of carefully selected patients. However, it carries substantial risks and is not a routine first treatment for CLL.
Clinical trials may provide access to new combinations, next-generation targeted therapies, cellular treatments, and strategies intended to produce deeper or longer remissions.
Evidence basis:
Possible Complications of CLL
Because CLL affects immune cells, infection is a major concern even when a patient has never received cancer therapy. The disease may reduce the production of effective antibodies, while some treatments further suppress immune defenses.
Other possible complications include:
- Anemia and low platelet counts caused by bone marrow crowding.
- Autoimmune hemolytic anemia, in which the immune system attacks red blood cells.
- Immune thrombocytopenia, in which platelets are mistakenly destroyed.
- An increased risk of certain second cancers, particularly skin cancer.
- Richter transformation, in which CLL changes into a faster-growing lymphoma.
Rapid lymph node enlargement, unexplained fever, sharply worsening fatigue, weight loss, or drenching night sweats should be reported promptly. These symptoms do not prove that transformation has occurred, but they deserve medical evaluation.
Evidence basis:
Living Well With CLL
Living with CLL involves more than watching laboratory numbers march across a patient portal. Preventive care, emotional support, and everyday health habits remain important throughout active surveillance and treatment.
Patients should discuss vaccinations with their hematology team because immune responses may be weaker and certain live vaccines may be inappropriate. Prompt evaluation of infections, regular skin examinations, routine cancer screenings, dental care, physical activity, adequate sleep, and balanced nutrition can support overall health.
No special diet has been proven to eliminate CLL. A practical eating plan generally emphasizes vegetables, fruit, whole grains, protein-rich foods, and sufficient calories. During treatment, food-safety precautions may become especially important.
Patients should also tell their oncology team about supplements and over-the-counter products. “Natural” does not automatically mean harmless, just as “made in a laboratory” does not automatically mean villainous. Some supplements can interact with targeted drugs or increase bleeding risk.
Evidence basis:
The CLL Experience: What the Journey Can Feel Like
The following scenarios are composites based on commonly reported experiences. They do not represent individual medical histories, and every person’s course is different.
Experience 1: The surprise diagnosis
A person visits a primary care clinic expecting a routine annual examination. The blood pressure is acceptable, the conversation about exercise is politely optimistic, and then the CBC shows an elevated lymphocyte count. Another blood test and flow cytometry follow. A few days later, the person hears the word “leukemia” despite feeling entirely healthy.
The emotional reaction may be far more dramatic than the physical condition. Patients can move rapidly between fear, disbelief, information overload, and irritation that everyone keeps saying the disease is “slow-growing” as though that makes the word cancer sound casual. It often helps to write down questions, bring another person to appointments, and ask the specialist to explain which findings matter now and which may matter later.
Experience 2: Adjusting to active surveillance
Being told that no treatment is needed can feel reassuring for approximately six seconds. Then the questions arrive: Why diagnose it if nothing is being done? Could treatment today prevent trouble tomorrow? What if the count rises before the next visit?
Over time, many patients learn that active surveillance is an organized medical strategy. Regular appointments create a rhythm. The care team tracks symptoms, lymph nodes, hemoglobin, platelets, and disease pace. The patient also learns that minor changes do not necessarily signal an emergency. A lymphocyte count can rise without requiring treatment, and one laboratory value rarely tells the entire story.
Experience 3: Learning the language
CLL comes with enough abbreviations to make a bowl of alphabet soup look underqualified: CBC, FISH, IGHV, TP53, BTK, BCL-2, MRD, and more. Early appointments may feel like attending an advanced biology lecture while someone quietly moves the final exam closer.
Patients often gain confidence by requesting copies of results and asking for plain-language explanations. “What does this test change?” is an especially useful question. Some findings help estimate how the disease may behave, while others directly influence treatment selection. Understanding that difference can prevent every flagged value from becoming a midnight internet expedition.
Experience 4: Starting treatment
After several stable years, a patient may develop worsening fatigue, enlarging lymph nodes, anemia, or uncomfortable spleen enlargement. Starting treatment can bring mixed emotions. There may be disappointment that surveillance has ended, relief that something active is being done, and concern about side effects.
The first weeks may involve medication schedules, laboratory checks, hydration instructions, and adjustments to other prescriptions. Side effects vary according to the regimen. Some are manageable with supportive care or dose changes, while others require prompt attention. Clear instructions about fever, unusual bleeding, heart symptoms, diarrhea, rash, or shortness of breath can make treatment feel less like navigating in heavy fog.
Experience 5: Living between appointments
CLL can become a long-term companion that was never invited to the party. It may periodically demand attention, but it does not need to occupy every room in a person’s life.
Many people continue working, traveling, exercising, caring for relatives, pursuing hobbies, and making plans. Emotional adjustment may take longer than physical adjustment. Some patients benefit from support groups, counseling, patient organizations, or conversations with others who understand the peculiar anxiety of waiting for laboratory results.
A useful goal is not to pretend that CLL is insignificant. It is to give the disease an appropriate amount of attention without allowing it to become the sole author of the future. Medical follow-up matters, but so do birthdays, ordinary Tuesdays, badly timed jokes, vacations, grandchildren, gardens, and whatever else makes life feel like life.
Evidence basis:
Conclusion
Chronic lymphocytic leukemia is a usually slow-growing cancer of lymphocytes that begins in blood-forming tissues. Its course varies widely. Some people need treatment soon after diagnosis, while others remain healthy under active surveillance for many years.
Blood counts, flow cytometry, genetic testing, symptoms, disease stage, and overall health help doctors understand how an individual case is behaving. When treatment becomes necessary, targeted therapies, monoclonal antibodies, and other modern approaches offer multiple ways to control the disease.
The most important lesson is that a CLL diagnosis is not a complete forecast. It is the beginning of a personalized monitoring and treatment plan. Good information, regular follow-up, preventive care, and open communication with a hematologist can replace at least some uncertainty with practical next steps.